
Blog
Fatty Liver Disease and Fatigue: Why an Overloaded Liver Could Be Draining Your Energy (2026 Guide)


Fatty Liver Disease and Fatigue: Why an Overloaded Liver Could Be Draining Your Energy
Fatty liver disease has a reputation for being harmless — something you find out about almost by accident, on a scan or a blood panel run for something else entirely. But ask people who actually have it what tipped them off, and an oddly high number say the same thing: it wasn't pain, it wasn't jaundice, it was a flat, unrelenting tiredness that diet and sleep never seemed to touch. Here's what's actually happening inside a fat-loaded liver, the lab number most checkups gloss over, and what's worth bringing up before your next appointment.
- Fatty liver disease (MASLD, formerly NAFLD) is fat buildup in the liver tied to obesity, insulin resistance, and metabolic dysfunction — not just alcohol, and it now affects roughly 1 in 3 adults worldwide.
- Fatigue is one of the most consistently reported symptoms, often years before any liver problem is suspected, because the liver itself has no pain nerves and stays silent until damage is advanced.
- A "normal" ALT or AST doesn't rule it out. Liver enzymes can look fine while fat and even fibrosis quietly build — a separate score called FIB-4 tracks this more reliably than enzymes alone.
- It's closely tied to insulin resistance, visceral fat, and low-grade inflammation, which is why it so often travels alongside type 2 diabetes, PCOS, and high triglycerides.
- Early-stage MASLD is genuinely reversible with weight loss, activity, and metabolic correction — this is one of the more hopeful diagnoses in this cluster if caught early.

1. Why Fatty Liver Fatigue Gets Missed
Most conditions that cause fatigue eventually announce themselves through some other symptom — pain, swelling, a fever, a number on a scale that won't move. Fatty liver disease is unusually good at staying quiet. The liver itself has no pain receptors on its surface tissue, so it can accumulate a meaningful amount of fat — sometimes 10, 20, even 30 percent of its mass — without sending a single warning signal you'd notice day to day.
Mayo Clinic Proceedings notes that people with uncomplicated fatty liver disease are typically asymptomatic, or their symptoms are vague, with fatigue and abdominal discomfort as the two most commonly reported complaints when anything is noticed at all. That vagueness is exactly the problem: a tired, slightly uncomfortable feeling gets absorbed into "I've just been busy" or "I'm not sleeping great" long before anyone thinks to check the liver — an organ most routine checkups only glance at through a general metabolic panel, not a dedicated evaluation.
2. The Liver-Metabolic-Fatigue Connection
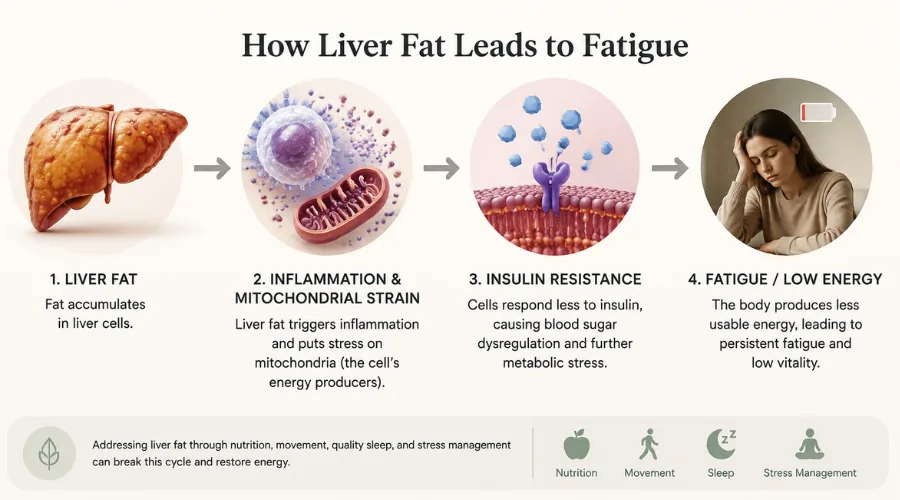
The link between a fatty liver and feeling exhausted isn't incidental — there's a plausible chain connecting the two. As fat accumulates inside liver cells, it strains the mitochondria that normally handle much of the body's energy processing, and it triggers low-grade, chronic inflammation as immune cells respond to the fat and cellular stress. That inflammatory signaling doesn't stay contained to the liver; circulating inflammatory markers are part of why systemic fatigue and a general sense of malaise show up even when someone otherwise feels "fine."
Fatty liver disease is also deeply intertwined with insulin resistance — in fact, many researchers now consider it a liver-based expression of the same metabolic dysfunction that drives type 2 diabetes. Cleveland Clinic explains that having obesity or type 2 diabetes are among the most common causes of this condition, now called MASLDMetabolic dysfunction-associated steatotic liver disease — the current medical term, which replaced "NAFLD" in 2023 to better reflect its metabolic origins rather than defining it by the absence of alcohol use., and that without treatment it can progress to more serious liver disease. When your cells struggle to respond properly to insulin, they struggle to take up and use glucose efficiently — which is a fairly direct route to feeling drained regardless of how much you slept.
- Genetics play a measurable role. Variants in genes like PNPLA3 are associated with a higher likelihood of fat accumulating in the liver, independent of body weight.
- Central (visceral) fat matters more than total body weight. Fat stored around the abdominal organs is more metabolically active and more strongly linked to liver fat than fat stored elsewhere.
- Rapid weight loss can trigger it too. Very fast fat mobilization — from crash diets or, less commonly, some bariatric recovery periods — can temporarily increase liver fat.
- Certain medications are recognized contributors, including some corticosteroids, tamoxifen, and specific chemotherapy agents — worth mentioning to a prescriber if a new medication coincides with new fatigue.
- Alcohol and metabolic risk can overlap. A newer category, MetALDMetabolic dysfunction and alcohol-associated liver disease — a 2023 classification for people who have both metabolic risk factors and moderate alcohol intake, sitting between MASLD and alcohol-related liver disease., describes people with both metabolic risk factors and moderate alcohol intake, which changes how the condition is evaluated and managed.
3. How Fatty Liver Disease Actually Progresses
Fatty liver disease isn't one fixed condition — it's a spectrum. Most people who have it sit at the earliest stage, simple steatosis, where fat is present but there's little or no inflammation, and this stage rarely causes serious liver damage on its own. In a smaller subset, the fat triggers ongoing inflammation and cell injury, a stage now called MASHMetabolic dysfunction-associated steatohepatitis — the more serious, inflamed form of fatty liver disease, previously called NASH. This is the stage most strongly linked to further liver damage. (formerly NASH), which can progress further to fibrosis and, in a minority of cases, cirrhosis.
A 2022 study of NAFLD patients published in Healthcare found that people with the condition reported significantly lower physical quality-of-life scores and significantly higher depression scores compared with healthy controls, with fatigue measured as a meaningfully affected domain — evidence that this isn't just a subjective complaint, but a measurable drop in day-to-day function. A separate small study using objective exercise testing found that people with the more inflamed MASH stage had reduced exercise capacity compared with those who had simple steatosis, suggesting the fatigue tracks with disease severity rather than staying flat across the whole spectrum.
4. Liver-Related Fatigue vs. Other Common Causes
Fatigue this common has a lot of competing explanations, and it's worth being honest about which features actually point toward the liver rather than assuming every tired, slightly uncomfortable feeling belongs here.
Fatigue plus metabolic risk factors and right-upper-quadrant heaviness
A flat, persistent tiredness that runs alongside excess weight (especially around the abdomen), prediabetes or diabetes, high triglycerides, or a dull ache or fullness under the right rib cage points toward the liver as a plausible contributor, particularly when standard sleep and thyroid checks come back unremarkable.
Fatigue with a clear, unrelated trigger or pattern
Fatigue that's sharply tied to a menstrual cycle phase, that improves dramatically with iron or B12 correction, that comes with an obvious sleep-disorder pattern, or that appeared abruptly after a specific viral illness points toward a different, more specific cause that deserves its own evaluation rather than being filed under "probably the liver."
These aren't mutually exclusive — fatty liver disease very commonly overlaps with diabetes, PCOS, and disrupted sleep, so more than one explanation can be true at once. The point of naming the distinction isn't to pick a single cause, but to make sure the liver isn't the one thing left off the list.
5. Patterns That Come Up Often

A pattern that comes up repeatedly involves someone whose annual bloodwork looked "basically fine" for years — cholesterol borderline, blood sugar borderline, nothing flagged as urgent — while a slow, low-grade tiredness quietly became the new normal. It was often a routine abdominal ultrasound for an unrelated reason that first showed fat in the liver, well before anyone had connected the dots to how exhausted they'd been feeling.
Another recognizable pattern involves someone with type 2 diabetes or prediabetes who assumed their fatigue was simply "part of managing diabetes," without realizing that a fatty liver can be actively working against their blood sugar control — and that improving one often measurably improves the other.
A third pattern involves someone who lost a meaningful amount of weight and was surprised that their fatigue improved dramatically before the scale changed much further — a reminder that liver fat and inflammation can start clearing with even modest, sustained weight loss, well ahead of larger changes in body composition.
These are illustrative patterns drawn from how fatty liver disease commonly presents, not accounts of specific individuals.
6. Who's Most Often Affected
People With Obesity or Excess Abdominal Fat
Excess visceral fat is one of the strongest and most consistent risk factors identified across major liver-health organizations.
People With Type 2 Diabetes or Prediabetes
Insulin resistance and fatty liver disease frequently occur together, and each can make the other harder to manage.
People With High Triglycerides or Low HDL Cholesterol
An abnormal lipid profile is one of the most common accompanying findings, and often the first clue on routine labs.
People With PCOS
The same insulin-resistance mechanisms that drive many PCOS symptoms also raise the risk of fatty liver disease, making the two conditions common companions rather than coincidences.
People With a Family History or Certain Genetic Variants
A family history of fatty liver disease, or known variants like PNPLA3, raises individual risk independent of body weight.
7. Interactions: The Lab Number Most Checkups Misread
This is the detail that changes how a "clean" lab report should actually be read. Most routine physicals check ALT and AST — two liver enzymes — and treat a result inside the reference range as reassurance that the liver is fine. That reassurance is often premature.
- Normal ALT/AST doesn't rule out significant fat or fibrosis. Liver enzymes can sit comfortably in the "normal" range for years while fat quietly accumulates, especially in women, older adults, and people with diabetes.
- FIB-4 is a simple, widely available score most patients have never heard of. Calculated from age, ALT, AST, and platelet count, it estimates the likelihood of significant liver fibrosis and is increasingly used as a first-line screening step before more expensive imaging.
- Imaging tells a fuller story than blood work alone. Ultrasound can detect fat, while specialized elastography (sometimes called a FibroScan) estimates stiffness — a proxy for scarring — without a biopsy in most cases.
- The liver-iron connection deserves a mention too. Elevated ferritin sometimes shows up alongside fatty liver disease as part of the same inflammatory picture, which is one reason a ferritin result should be interpreted alongside the full metabolic picture rather than in isolation — the ferritin threshold itself is covered in more depth in our Ferritin Test Explained guide.
- Metformin, statins, and moderate alcohol all deserve an honest conversation with a prescriber. None are automatically off the table for someone with fatty liver disease, but each interacts with liver health in ways worth reviewing individually rather than assuming or avoiding by default.
If your last physical included a liver enzyme panel that came back "normal," ask what your actual ALT and AST numbers were, and whether a FIB-4 score has ever been calculated from them. The math takes seconds and often changes the conversation.
8. Real-World Scenarios: Where Do You Fit?
"My bloodwork is basically normal, but I'm constantly drained and carry weight around my middle."
Worth asking specifically about a FIB-4 score and a liver ultrasound rather than assuming normal enzymes settle the question (see Section 7).
"I have type 2 diabetes and just assumed the fatigue was part of that."
Fatty liver disease and diabetes commonly reinforce each other — it's worth asking whether liver fat has ever specifically been evaluated (Section 2 and Section 6).
"I have PCOS and I'm always exhausted, even on good sleep."
The same insulin-resistance pathway links both conditions — see Section 6, and our dedicated PCOS and Fatigue guide for the reproductive-hormone side of this picture.
"I lost some weight and my energy came back faster than I expected."
A recognized and encouraging pattern — liver fat and inflammation can begin improving with modest, sustained weight loss, described in Section 3 and Section 14.
9. How Fatty Liver Disease Is Actually Diagnosed
Unlike some conditions with a single confirmatory test, fatty liver disease is typically identified through a step-up process rather than one decisive result.
| Step | What it involves |
|---|---|
| 1. Risk review | A clinician considers weight, waist circumference, diabetes status, lipid panel, and alcohol intake. |
| 2. Liver enzymes + FIB-4 | ALT and AST are checked, then combined with age and platelet count to calculate a FIB-4 score estimating fibrosis risk. |
| 3. Imaging | Ultrasound detects fat; elastography (FibroScan) or specialized MRI estimates liver stiffness without a biopsy in most cases. |
| 4. Ruling out other liver causes | Viral hepatitis, autoimmune liver disease, and iron-overload conditions are typically excluded before confirming MASLD. |
| 5. Biopsy (uncommon) | Reserved for cases where imaging and blood work leave real uncertainty about the stage of fibrosis, or where treatment decisions hinge on a precise answer. |
The most common trap in this process is stopping at step one or two — treating a normal-looking enzyme panel as the end of the conversation, rather than the beginning of it, particularly for someone who already carries several metabolic risk factors from Section 6.
A liver ultrasound ordered for an unrelated reason — a gallbladder concern, a routine abdominal scan — is one of the most common ways fatty liver disease is actually discovered. If you've had one recently for any reason, it's worth asking specifically what it showed about your liver, not just the organ it was ordered to check.
10. Try It: Liver-Risk Pattern Finder
Which best describes your situation?
Tap the option that fits best to see what that pattern often points to.
Not a diagnostic tool — for education only. Bring your specific pattern to a clinician.
11. What to Track Before Your Next Appointment

Write down your actual ALT and AST numbers
Not just whether they were flagged — the numbers themselves make a FIB-4 calculation possible (Section 7).
Note your waist circumference, not just your weight
Central fat is more predictive of liver risk than total body weight, described in Section 2.
Log your fatigue alongside meals and activity
A simple daily rating helps separate liver-related fatigue from a purely sleep-driven pattern (Section 4).
Track your average weekly alcohol intake honestly
This changes how your risk is categorized (MASLD vs. MetALD) and how it should be managed, described in Section 2.
📋 Print or save: "What to Tell Your Doctor" checklist
Bring this list to your appointment, or take a screenshot.
- Your most recent ALT and AST numbers (not just "normal" or "flagged")
- Whether a FIB-4 score has ever been calculated for you
- Your waist circumference, blood pressure, and most recent lipid panel
- Any diagnosis of prediabetes, type 2 diabetes, or PCOS
- Your honest average weekly alcohol intake
- Any new medications started in the past year (Section 2)
- Family history of fatty liver disease or other liver conditions
- How your fatigue has trended alongside any recent weight changes
12. The 2026/2027 Edge: Where Fatty Liver Care Is Heading

Terminology itself has shifted recently — "NAFLD" and "NASH" were formally renamed MASLD and MASH in 2023 to better reflect the metabolic origins of the condition, and clinical guidance has continued adapting to that framework. Treatment options have also expanded: resmetirom, a thyroid hormone receptor-beta agonist, became the first medication specifically approved for MASH with moderate-to-advanced fibrosis, while GLP-1 receptor agonists originally developed for diabetes and weight management are being studied and used for their liver-fat-reducing effects as part of broader metabolic treatment plans.
FIB-4 and other non-invasive fibrosis scores have become more central to primary-care screening, with some health systems now calculating them automatically from routine bloodwork rather than waiting for a specialist referral — part of a broader push toward catching liver fat earlier, while it's still fully reversible, rather than after fibrosis has set in.
None of this changes the core standard of care: a proper evaluation still relies on the step-up process in Section 9, and lifestyle change — not a pill — remains the foundation of management for the vast majority of people at the earlier, more common stages.
13. Red Flag Symptoms: When Fatigue Requires Immediate Medical Evaluation
Most fatty liver disease is silent and not immediately dangerous. Certain patterns call for faster evaluation rather than waiting for a routine appointment:
- Yellowing of the skin or eyes (jaundice), which always warrants prompt medical evaluation.
- Sudden or severe pain in the upper right abdomen, rather than a mild ache, which needs urgent assessment.
- Noticeable swelling of the abdomen or legs, or unexplained, significant unintentional weight loss.
- New confusion, disorientation, or unusual drowsiness, which can indicate a serious liver complication and needs immediate medical attention.
- Vomiting blood or passing black, tarry stools, which are emergency symptoms requiring immediate care.
- Significant, worsening low mood or thoughts of self-harm alongside chronic fatigue — this always warrants prompt professional support regardless of the underlying cause.
14. What Actually Helps, Beyond the Diagnosis
Cleveland Clinic notes that steatotic liver disease is often reversible, especially in earlier stages, and that treatment typically focuses on managing the underlying metabolic conditions driving it rather than treating the liver in isolation.
Aim for gradual, sustained weight loss if you carry excess weight
Losing even 5–10% of body weight is associated with measurable reductions in liver fat, and many people notice fatigue improving well before larger changes appear on the scale (Section 3).
Shift toward a Mediterranean-style eating pattern
Higher intake of vegetables, whole grains, and unsaturated fats, with less added sugar and refined carbohydrate, is consistently linked with lower liver fat.
Build regular movement into your week
Both aerobic activity and resistance training are associated with liver-fat reduction, independent of weight change in some studies.
Review alcohol intake honestly with a clinician
Even moderate drinking can meaningfully interact with existing metabolic liver risk (the MetALD category from Section 2), so this is worth an honest conversation rather than a guess.
Support your broader metabolic wind-down routine
Many people managing metabolic and energy concerns also pay attention to magnesium intake as part of a broader routine — our Magnesium Deficiency and Fatigue guide covers that separately. Always discuss new supplements with your clinician, especially with existing liver findings.
15. Decision Guide — Your Situation, Your Next Step
| Your situation | Most relevant next step |
|---|---|
| Constant fatigue, central weight gain, "normal" bloodwork | Ask for your actual ALT/AST numbers and a FIB-4 calculation, not just a pass/fail read (Section 7). |
| Diabetes or prediabetes already diagnosed | Ask whether liver fat has specifically been evaluated, since the two conditions commonly reinforce each other (Section 6). |
| PCOS diagnosis with ongoing fatigue | Raise the insulin-resistance connection directly with your provider (Section 6). |
| Recent ultrasound for an unrelated reason | Ask specifically what it showed about your liver, not just the organ it targeted (Section 9). |
| Regular alcohol use alongside metabolic risk factors | Have an honest conversation about the MetALD category and what it means for your specific risk (Section 2). |
16. Frequently Asked Questions
Can fatty liver disease really cause fatigue if my liver tests are normal?
Is fatty liver disease the same thing as NAFLD?
Do I have to drink alcohol to get fatty liver disease?
Can fatty liver disease be reversed?
What test should I ask for if I suspect fatty liver disease?
When should I see a doctor about possible fatty liver disease?
Ask about your liver, not just your weight
- Fatty liver fatigue starts silently — the liver has no pain nerves, so fat can build up for years without an obvious warning sign.
- "Normal" ALT/AST doesn't settle the question — ask for the actual numbers and a FIB-4 calculation.
- It's inseparable from metabolic health — diabetes, PCOS, and high triglycerides are frequent companions, not coincidences.
- Diagnosis is a step-up process — enzymes, fibrosis scores, and imaging together, not any single test alone.
- Early-stage disease is genuinely reversible — weight loss, diet, and activity remain the foundation of treatment for most people.

Milk Thistle (Silymarin) Capsules
A traditional liver-support herb studied in some small trials; evidence for meaningful clinical benefit in MASLD remains limited.
Check price
NAC (N-Acetylcysteine) Capsules
An antioxidant precursor sometimes discussed for liver and metabolic support; ask your clinician before combining with other medications.
Check price
Vitamin E (Mixed Tocopherols) Softgels
The one supplement with real trial evidence in non-diabetic MASH under medical guidance — not a general recommendation without a clinician's input.
Check priceReferences
- Cleveland Clinic — MASLD (Nonalcoholic Fatty Liver Disease). clevelandclinic.org — MASLD
- Cleveland Clinic — Steatotic (Fatty) Liver Disease: Symptoms & Treatment. clevelandclinic.org — Fatty Liver Disease
- Mayo Clinic Proceedings — Nonalcoholic Fatty Liver Disease: Review of Management for Primary Care Providers. mayoclinicproceedings.org — NAFLD Review
- Johns Hopkins Medicine — Nonalcoholic Fatty Liver Disease. hopkinsmedicine.org — NAFLD
- American Liver Foundation — Nonalcoholic Fatty Liver Disease (NAFLD). liverfoundation.org — NAFLD
Written by the HealthBoostOne Editorial Team
Fact-checked against Cleveland Clinic, Mayo Clinic, Johns Hopkins Medicine, and American Liver Foundation patient guidance.
Last reviewed: August 2026. This article is for general information and does not replace individualized advice from a licensed clinician.


3 thoughts on “Fatty Liver Disease and Fatigue: Why an Overloaded Liver Could Be Draining Your Energy (2026 Guide)”